
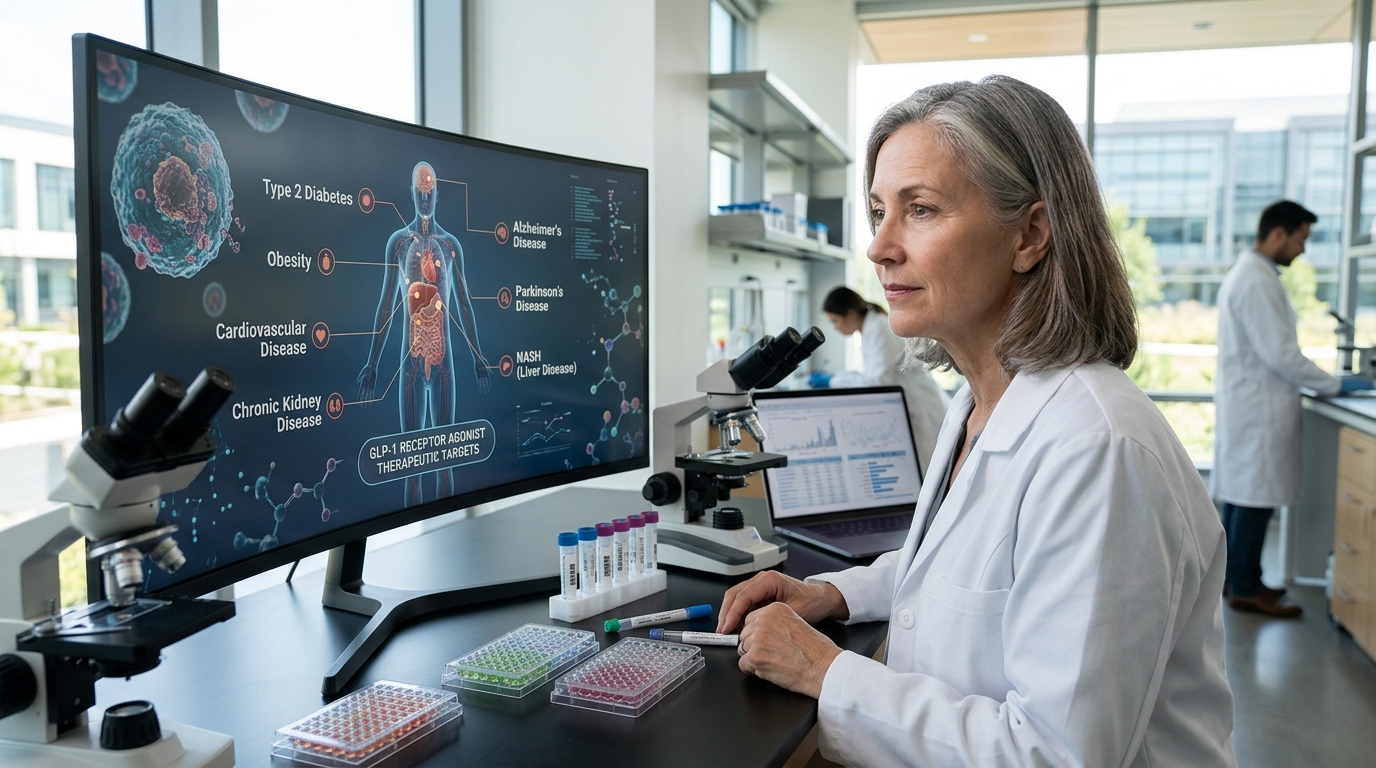
The geriatric medicines market sits at $190.7 billion today and is on track to reach $340 billion by 2034. That is not a forecast built on hope. It is arithmetic: about 10,000 Americans turn 65 every day, and the diseases that cluster in older bodies, metabolic, cardiovascular, neurological, are now converging around a single, increasingly powerful class of drugs.
GLP-1 receptor agonists started as glucose regulators. Over the past three years, the evidence has broadened dramatically. Semaglutide’s SELECT trial, which enrolled 17,604 adults with cardiovascular disease and obesity, showed a 20% reduction in major heart events, independent of any diabetes diagnosis. The FLOW trial added a 24% reduction in major kidney outcomes. A 2026 randomized controlled trial published in Nature Communications reported significantly less epigenetic aging with semaglutide than placebo on multiple validated epigenetic clocks, in a 32-week trial in people with HIV-associated lipohypertrophy. The drug that Novo Nordisk originally designed to lower blood sugar is now generating data across the entire spectrum of age-related disease.
The Oral Revolution Changes the Access Equation
For years, injectable delivery kept GLP-1 penetration low. Eli Lilly estimates that fewer than 1 in 10 people who could benefit from a GLP-1 are currently taking one. That bottleneck cracked open in April 2026, when the FDA approved Foundayo (orforglipron), a once-daily GLP-1 pill for weight loss that can be taken at any time of day without food or water restrictions. Self-pay pricing starts at $149 per month; Medicare Part D patients can access it for $50 per month beginning July 2026. Novo Nordisk’s oral Wegovy, approved in December 2025, competes directly.
Oral delivery is not just a convenience. It is the difference between a therapy that reaches tens of millions of older Americans and one that stays confined to specialist offices.
The Triple Agonist: Where the Pipeline Gets Genuinely Surprising
Lilly’s next candidate, retatrutide, simultaneously activates three hormone receptors: GLP-1, GIP, and glucagon. The TRIUMPH-1 Phase 3 trial, reported in May 2026, hit every primary and secondary endpoint for obesity at 80 weeks. Seven additional Phase 3 readouts from the TRIUMPH program are expected before year-end, covering type 2 diabetes, sleep apnea, cardiovascular risk, and liver disease. Retatrutide is not yet approved, but the pipeline breadth matters: a single weekly injection that addresses obesity, arthritis pain, liver inflammation, and cardiovascular risk simultaneously is exactly what aging patients and their insurers need.
Alzheimer’s: A Bigger, Harder, and More Lucrative Battleground
The neurodegenerative front is more complicated. The anti-amyloid antibodies Leqembi and Kisunla have crossed $1 billion in combined annualized global sales, with Leqembi posting 74% year-over-year growth in Q1 2026 in global in-market sales, reaching $168 million in a single quarter. The global Alzheimer’s drug market is projected to hit $38.5 billion by 2034. With an estimated 7.4 million Americans aged 65 and older currently living with Alzheimer’s, Medicare covers both antibodies under its coverage framework. In July 2026, the FDA approved a new starting dosage regimen for the subcutaneous (under the skin) formulation of Leqembi, aimed at improving at-home initiation.
GLP-1s tried to extend their reach into Alzheimer’s and stumbled: two Phase 3 semaglutide trials in AD patients failed to slow clinical progression. But a liraglutide Phase 2 trial has shown signals consistent with slower cognitive decline over one year, and next-generation brain-penetrant agonists are entering clinical development. The failure of semaglutide in AD is not a verdict against the class; it is an argument for better-designed molecules targeting the same underlying biology of neuroinflammation and insulin resistance in the brain.
Where Investors Should Be Looking
Eli Lilly’s 2026 revenue guidance of $80 billion to $83 billion reflects a company that has effectively bet its franchise on aging-population pharmacology, and Mounjaro and Zepbound together accounted for 65% of revenue for the first half of 2026. The pipeline behind those products, from Foundayo through retatrutide and Kisunla, represents compounding market exposure across metabolic, cardiovascular, and cognitive disease. Biogen’s Leqembi franchise and the broader anti-amyloid class offer a second exposure point, particularly as blood-based biomarker diagnostics expand the addressable patient population. The real risk is execution speed: infrastructure for infusions, physician training, and insurance coverage remain the friction points slowing adoption.
Risks to Watch
Muscle loss during rapid GLP-1-driven weight reduction remains a genuine clinical concern, particularly in frail elderly patients. Long-term neurodegenerative data in healthy non-obese populations does not yet exist. Anti-amyloid antibody risks, brain swelling and micro-bleeds, are more common in carriers of the ApoE4 gene variant, limiting the addressable market. And while some key semaglutide patents have expiries in the early 2030s in the U.S., generic competition is still years away, keeping access gaps real.
Wealth Takeaway
The aging global population is not a theme. It is a structural demand floor that grows every year regardless of economic cycles. The companies building multi-indication pipelines around GLP-1 and anti-amyloid biology are not chasing a single blockbuster; they are building compounding revenue streams across the full spectrum of age-related disease. That is the kind of durable market position worth analyzing before the next indication approval lands, not after.



